Osteoarthritis is common, it gets more common every decade, and it is often described as wear and tear. All of that is true and none of it is the whole picture. Here is what is actually happening in the joint, why some people get it badly and others barely notice, and what genuinely changes the outcome.
What osteoarthritis actually is
Osteoarthritis is the slow breakdown of cartilage, the smooth tissue that lines the ends of bones inside a joint. Cartilage lets one bone slide over the other without friction, and it absorbs impact like a shock absorber.
When that cartilage thins, the joint loses its cushioning. The body responds by changing the bone and soft tissue around it, which is why scans show thickening, bony spurs and uneven joint spaces. It is a remodelling process, not simply a surface wearing away.
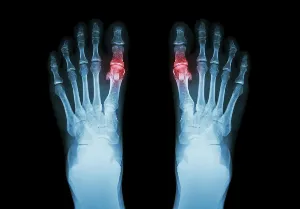
It is the most common form of arthritis by a wide margin. Around one in thirteen Australians report having it, and two thirds of those are women. Knees and hips are the most commonly affected and usually the most symptomatic, followed by the fingers, thumbs, big toes and lower back.
Is it wear and tear?
Partly, but that framing causes real problems.
“Wear and tear” suggests a joint is being used up, like brake pads. It implies the fix is to stop using it. That is the opposite of what helps. Joints need movement to stay healthy, because the fluid that lubricates them is produced in response to movement. A joint you stop using gets stiffer, not better.
It is more useful to think of it as the joint’s capacity to maintain itself falling behind the load going through it. That is a balance, and a balance is something you can shift.
Why it gets more common with age
Three things stack up as the years go on.
Prevalence rises steeply. Osteoarthritis is uncommon under 40 and increasingly common every decade after. By the time you are in your seventies, most people have changes in at least one joint.
Cartilage repairs itself less well. The cells that maintain cartilage slow down with age and become less efficient, so the tissue has less chance to keep up with the demands placed on it.
Load accumulates. A lifetime of movement, plus any old injuries, plus any extra weight, plus whatever your job asks of your body. None of these is decisive alone. Together they are what tips the balance.
Why some people get it and others do not
This is the question people actually want answered, and the honest answer is that several things contribute and no single one decides it.
Genetics matter more than people expect. Joint shape, cartilage quality and how readily a body lays down new bone are all partly inherited. If your parents had arthritic knees, that is worth knowing.
Old injuries count. A joint that has had a significant injury, especially to the cartilage or ligaments, is far more likely to develop osteoarthritis later. A knee you snapped in your twenties can show up in your fifties.
Weight is the biggest factor you can change. Every extra kilogram multiplies through the hip and knee with each step. This is not about blame, it is about where the most leverage is.
What your job and sport ask of you. Repeated deep squatting, kneeling and heavy lifting load joints in ways that add up. So does high-impact running on joints that are already struggling, though running itself is far less damaging to healthy joints than most people assume.
What it is not
It is worth being clear, because the confusion is extremely common and it changes what treatment makes sense.
Osteoarthritis is not rheumatoid arthritis. They are entirely different diseases. Rheumatoid arthritis is an autoimmune condition where the immune system attacks the joint lining, often symmetrically across both sides of the body, often with whole-body symptoms. Osteoarthritis is a local mechanical and biological process in one or more specific joints.
If you have had scan language thrown at you and are not sure which you are dealing with, we have written up the difference and the common scan terms separately, in osteoarthritis and Pilates and in what those scan words actually mean.
What actually changes the outcome
Here is the part worth holding onto. Osteoarthritis is not curable, but it is very manageable, and the things that help are not mysterious.
Keep moving. This is the single best-supported treatment. Movement produces the fluid that lubricates the joint and keeps the surrounding muscles doing their share of the work. Resting an arthritic joint makes it worse.
Build strength around it. Strong muscles take load off the joint itself. This is the mechanism behind most of the benefit from exercise, and it is why a targeted program beats general activity.
Manage the load rather than avoid it. Too much of the wrong thing flares it up. Too little stiffens it. The work is finding the amount you can do consistently, which is exactly what a physio helps you calibrate.
Address weight if it is relevant. Not as a moral point. As the one factor that changes the maths on every single step.
Treat flare-ups properly. A bad week is not a setback, and pushing through it usually makes it longer. Knowing how to settle a flare and then get moving again is a skill, and it is teachable.
Where to go from here
- What exercise and Pilates do for arthritic joints — the practical side, including why strength matters more than stretching
- Those scary words on your scan report — osteophytes, cortical thickening and the rest, translated
- Knee arthritis and what physio does about it — the joint most people ask about first
If it is your hip or knee that is the problem, our hip pain and knee injury pages set out how we approach those specifically, and lower back pain covers the spine. Arthritis is behind a large share of what we see in all three.
To keep moving without hammering sore joints, our 30 Minute Hip and Lower Back Reset class is gentle, controlled and built for stiff joints.