Relaxin does exactly what its name suggests, and it is one of the reasons your pelvis can open enough to let a baby through. It is also the reason a lot of pregnant women are told their pelvis has gone loose or slipped out of position. That second part is where the story usually goes wrong, so it is worth separating the two.
Your pelvis is not falling apart. Pregnancy-related pelvic girdle pain is real, common and worth treating properly, but it is not a joint that has come out of alignment and needs pushing back in.
What relaxin actually does
Relaxin is produced by the ovaries in early pregnancy and then by the placenta. Levels are highest in the first trimester, fall in the middle, then climb again near term. Both men and women make small amounts of it, and it got its name from what it does in pregnancy.
Its job is to let connective tissue remodel, which is what allows the pubic bones to part slightly during birth and the cervix to soften. It also relaxes blood vessel walls, which helps the body move far more blood around than it is used to.
That much is straightforward. The stretchier-tissue explanation for pain is where it gets overstretched.
Why looser ligaments are not the whole explanation
For years the standard advice was that relaxin loosened the pelvic ligaments, the pelvis became unstable, the bones shifted, and the pain came from them being in the wrong place. The treatment that followed was to stabilise things and get the bones back.
Research has not held that up. European guidelines on pelvic girdle pain, and the clinical practice guidelines from the American Physical Therapy Association, both moved away from that framing. Reviews of the evidence, including work by Sinead Dufour and colleagues at McMaster University, argue that the instability concept is not substantiated and that it can do real harm by leaving women frightened of moving.
The current understanding is that pregnancy-related pelvic girdle pain is driven by a mix of things rather than a mechanical fault: how the load through your pelvis changes as you grow, the different ways you end up moving with a bump, sleep, stress, how sensitive your nervous system already is, and general health. The pain is genuine. The explanation for it has simply changed.
If you want the myth-busting version in more detail, we wrote it up separately in pelvic pain in pregnancy.
Where the pain actually shows up
It is felt in two places, and most people recognise themselves in one of them.
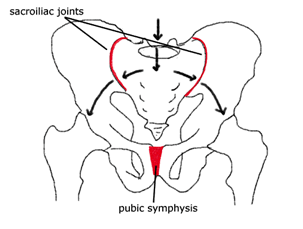
At the front, at the joint between your two pubic bones, is where pubic pain sits. It is sharpest when you are loading the two sides unevenly, which is why rolling in bed, getting out of a car and climbing stairs are the classic triggers.
At the back, beside your tailbone in the little dimples, is where sacroiliac pain sits. It tends to ache into the lower back, buttock or thigh, and it bites when you stand on one leg while moving the other. Walking, standing up from a chair, and getting dressed are the usual complaints.
Either can refer pain somewhere that feels far more serious than it is. Aching in the buttock or thigh does not mean something is trapped or damaged.
What helps
Treatment is the same whichever end it comes from, and it is not about putting anything back into place.
Moving is the most useful thing you can do, even though it sounds like the opposite of what the pain suggests. Short rest during a flare-up is fine. Staying off your feet for the rest of the pregnancy is not, because you lose the hip and leg strength you need to carry the extra load. Exercise is the treatment, not the reward for getting better.
We start by finding the movements you can do comfortably and building from there. Strength in the hips, legs and upper body matters more than anything targeting the pelvis directly, because those are the muscles doing the work of holding you up as the weight shifts. Our pregnancy classes are built around exactly that, graded so you are working within a pain range you can tolerate.
Support garments help some women. A pelvic belt or compression shorts do not hold your bones together, but they reduce the load on painful movements and can be enough to keep you moving when you otherwise would not. Our physios can tell you whether one is worth trying and how to fit it properly.
Small changes to how you do things make a surprising difference. Put your trousers, shoes and socks on sitting down rather than balancing on one leg. Sleep with a pillow between your knees. Take stairs one at a time, leading with the same leg each time rather than alternating.
And if you are in too much pain to start any of that, hands-on physiotherapy plus a graded exercise plan is usually what gets you back to moving.
How long it lasts
This is the part worth holding onto. In a large Norwegian study following more than 41,000 women who reported pelvic girdle pain at 30 weeks, 78% had recovered six months after giving birth. A further 18.5% had some pain left in one or two spots. Only 3% still met the definition of pelvic girdle syndrome.
So the outcome for most women is good, and it happens without anything dramatic being done. The point of treatment is not to rescue you from a broken pelvis. It is to make the months before that recovery arrive a great deal more liveable, and to get the smaller group who do not settle quickly back on track sooner.
If you are dealing with this now, our Letting Go of Pelvic Pain classes are physio-led and built for pregnancy, so you can start them at home.
New to Pilates? Begin with our Pilates Fundamentals for Pregnancy tutorials.
Refs: Vleeming et al. (2008), European guidelines for the diagnosis and treatment of pelvic girdle pain, European Spine Journal; Clinton et al. (2016), Pelvic girdle pain in the antepartum population, clinical practice guidelines, American Physical Therapy Association; Dufour and Britnell (2018), Pregnancy-related pelvic girdle pain: embrace the evidence and move beyond biomechanics; Vølestad et al. (2012), The effect of emotional distress on persistent pelvic girdle pain after delivery, BJOG.